Gout is not just a sore toe — it is a metabolic condition driven by insulin resistance, fructose, alcohol and dehydration. Here is how Siddha medicine for gout targets uric acid at the root, what the evidence supports, and a 12-week plan built for working professionals.
You wake at 3 a.m. with a big toe that feels like it has been hit with a hammer. The sheet touching it is unbearable. By morning it is red, swollen and hot, and you cannot put weight on it. Then, three days later, it is gone — and you go back to the same desk, the same late dinners and the same two litres of water you meant to drink but didn't.
That is gout, and in India it is no longer a disease of the very rich or the very old. It is now a metabolic condition that lands squarely on working professionals in their thirties, forties and fifties — men especially — who sit for nine hours, eat out four times a week and already carry a rising waistline and mildly abnormal blood sugar.
This guide explains what gout really is, why it keeps coming back, and what a Siddha medicine approach to uric acid looks like — including what the evidence honestly supports and what it does not.
Quick answer: Gout is caused by uric acid crystals forming in a joint when urate levels stay high — and urate rises mainly because of insulin resistance, excess fructose and alcohol, dehydration, and being overweight, not only because of "purine-rich food". Siddha treatment for gout combines supervised internal herbal medicines and external therapies with the changes that actually lower urate: 5–10% weight loss, cutting sugary drinks and alcohol, 2.5–3 litres of water a day, 150 minutes of weekly activity and better sleep. Most people see flares become less frequent within 8–12 weeks, but urate takes longer to normalise and existing tophi take months.
Why Gout Is a Metabolic Problem, Not Just a Joint Problem
Uric acid is the end product of purine breakdown. When blood urate stays above roughly 6.8 mg/dL, it can crystallise. The crystals are what your immune system attacks — and that attack is the flare.
What most people are never told is where the urate comes from. Only about 20–25% of it comes from food. The rest is produced internally, and its level is governed by how efficiently your kidneys excrete it. That is why a person eating a modest diet can still have stubbornly high uric acid — and why "stop eating dal" rarely fixes anything.
The uric acid–insulin resistance loop
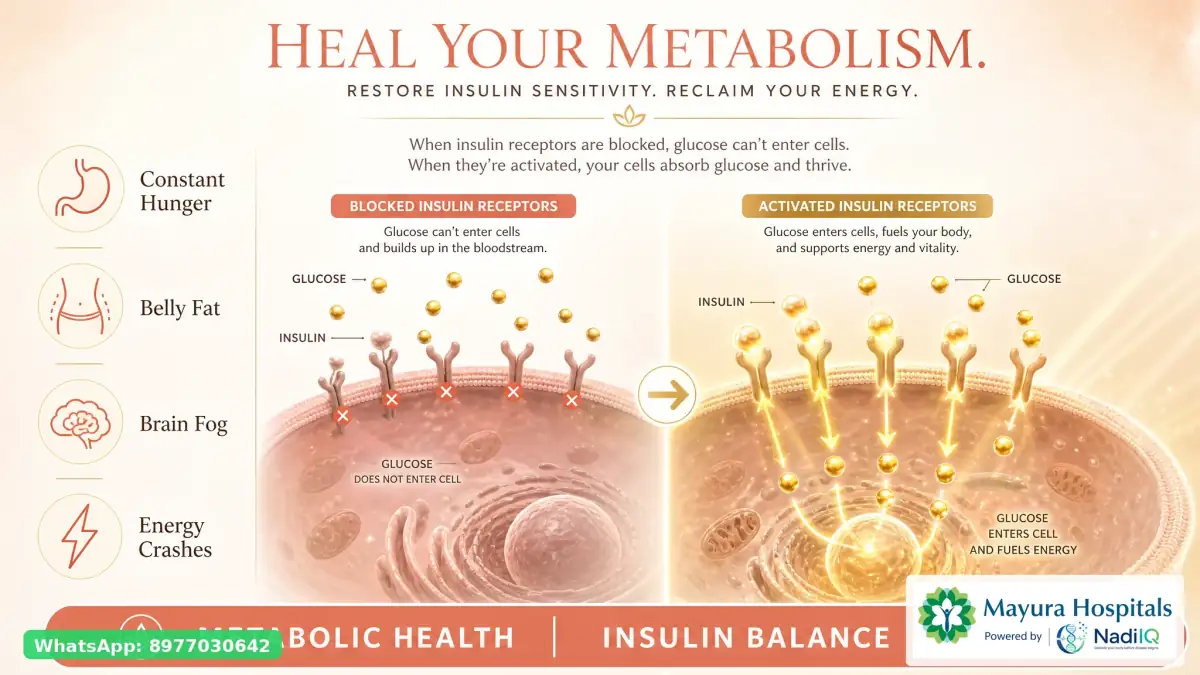
Insulin resistance reduces the kidney's ability to excrete urate. At the same time, high urate itself worsens insulin resistance and inflammation. The result is a loop: pre-diabetes raises urate, and raised urate makes blood sugar harder to control. A 2024 review in Signal Transduction and Targeted Therapy sets out this bidirectional mechanism in detail (Du et al., 2024).
This is why gout so often arrives alongside high blood pressure, abnormal lipids, central obesity and kidney stones. A European review of hyperuricaemia across cardiovascular, metabolic and kidney disease describes gout as a marker of exactly this cluster (Borghi et al., Eur J Intern Med, 2020).
Why Indian professionals are getting gout earlier
The global burden analysis published in The Lancet Rheumatology shows gout prevalence rising worldwide, with the steepest increases in middle-income countries and in men aged 30–59 (GBD 2021 Gout Collaborators, 2024). Indian data point the same way: a study of Indian adults with hypertension found hyperuricaemia in a substantial share of them (Patni et al., J Assoc Physicians India, 2023).
Four things drive it in this group: fructose from soft drinks, packaged juices and sweetened "health" drinks; alcohol, especially beer; chronic mild dehydration from coffee and air-conditioned offices; and visceral fat. Add a desk job, short sleep and high stress, and you have the perfect metabolic setup for a first attack at 38 rather than 68.
Gout Symptoms: What a Flare Actually Feels Like
A classic flare is unmistakable: sudden, severe pain in one joint — most often the base of the big toe — with redness, swelling, heat and extreme tenderness. It usually peaks within 12–24 hours and settles over 3–10 days even without treatment — which is why so many people ignore it.
Warning signs before the first attack
- A joint that aches or feels "bruised" for a few days before the attack
- Repeated episodes of a stiff, swollen toe or ankle that resolve on their own
- Uric acid above 7 mg/dL on a routine health check, with no symptoms at all
- Small firm lumps near joints, elbows or the rim of the ear (tophi) — a sign of long-standing high urate
- Kidney stones, especially urate stones, in someone with high urate
Asymptomatic hyperuricaemia does not always need drug treatment, but it is a signal worth acting on.
When it is not gout — red flags
See a physician urgently if a hot swollen joint comes with fever or chills (this can be infection, which is an emergency), if the joint is a knee, hip or spine rather than a toe, if you have kidney disease or are on diuretics, or if you are already on urate-lowering medication and still flaring. Gout is a clinical diagnosis; joint aspiration is the only way to be certain.
How Siddha Medicine Approaches Gout
In Siddha, joint disease of this type is understood within the keelvayu group of vaatham-dominant disorders; Ayurveda describes the same clinical picture as vatarakta. Both traditions read it as a whole-body problem: deranged vaatham, sluggish digestion (agni), accumulated metabolic waste, and a body that is not eliminating properly.
That framing is closer to modern understanding than it first appears. Siddha does not treat gout as "a toe problem" — it treats it as a metabolic and elimination problem that shows up in a toe.
Internal medicines
A Siddha physician works from the patient's naadi (pulse), digestion, urine, sleep and history, then prescribes from the classical pharmacopoeia — chooranam (powders), kudineer (decoctions), mezhugu (waxy pills) and parpam (purified mineral preparations). Several of the herbs used have published laboratory or human data:
- Seenthil / Guduchi (Tinospora cordifolia) — traditionally the lead herb for urate disorders; laboratory work has identified anti-gout activity in its constituents (3 Biotech, 2018).
- Nellikai (Phyllanthus emblica) — animal and mechanistic studies show protective effects in acute gouty arthritis (Evid Based Complement Alternat Med, 2022).
- Manjal / turmeric (Curcuma longa) — curcumin has been tested in humans for urate lowering (see below).
- Keezhanelli (Phyllanthus niruri) — widely used in Siddha for urinary and stone-related complaints.
None of these is a substitute for diagnosis. Parpam and mezhugu preparations contain purified metals and minerals and must never be self-prescribed or bought online.
External therapies
During a flare, Siddha practice favours gentle local measures — pattru (medicated poultice), ottradam (fomentation), and thylam application — rather than vigorous massage, which can worsen an acutely inflamed joint. Once the flare has settled, thokkanam and varmam work is used to restore movement and reduce stiffness. If you have chronic knee or joint pain alongside gout, our joint and spine pain programme covers that side of the picture.
What the Evidence Actually Says
Honesty matters more than enthusiasm here, so here is the state of the evidence in three parts.
Traditional medicine: promising but small
A clinical study of an Ayurvedic treatment protocol in gouty arthritis reported meaningful improvement in pain and joint scores (Vaprath Kuniyil et al., J Complement Integr Med, 2023). It is a small, single-centre study — encouraging, not definitive. Siddha-specific randomised trials for gout are scarce. That is a gap in the literature, not proof of failure, but it does mean your expectations should be calibrated.
Herbs with human data
The strongest human signal among the commonly used herbs is curcumin. A randomised, placebo-controlled trial in people with asymptomatic hyperuricaemia found a significant reduction in serum urate with curcumin supplementation (Bupparenoo et al., J Diet Suppl, 2021). It was a single trial in a specific population — useful supporting evidence, not a cure claim.
Diet: well established
Diet is where the evidence is strongest and least controversial. A review in Best Practice & Research in Clinical Rheumatology concludes that reducing alcohol (especially beer), sugar-sweetened beverages and fructose, and losing weight, lower urate — while the effect of strict purine restriction alone is modest (Danve et al., 2021). In other words, the modern evidence and the traditional "fix your digestion and your inputs" advice point in the same direction.
Siddha Care vs Conventional Care for Gout
Conventional care
- Acute flare: NSAIDs, colchicine or steroids to control inflammation fast
- Long term: allopurinol or febuxostat to lower urate; target usually below 6 mg/dL
- Strength: fast, well-evidenced, measurable, prevents joint damage and tophi
- Limits: does not address the insulin resistance, weight, sleep and diet driving the urate
Siddha care
- Acute flare: internal anti-inflammatory formulations plus pattru and ottradam; flares are usually still managed with conventional anti-inflammatories
- Long term: personalised pathiyam (diet), digestive correction, herbal therapy, thokkanam and varmam
- Strength: treats the metabolic and lifestyle root, improves digestion, sleep and mobility
- Limits: slower to act on urate; fewer large trials; requires a qualified physician
The honest position is that these are not rivals. The fastest way to stop a flare is conventional. The most durable way to stop the next one is to fix the metabolism underneath — and that is where Siddha care, delivered properly, earns its place.
The 12-Week Root-Cause Plan
Weeks 1–4: settle the flare, clean up the inputs
- Get the acute flare treated properly — do not "wait it out" if pain is severe.
- Stop alcohol completely for the first month, especially beer and spirits.
- Remove sugar-sweetened drinks, packaged juices and fructose-sweetened "health" drinks.
- Drink 2.5–3 litres of water daily; more in summer or if you train.
- Keep coffee to 2 cups; coffee is not harmful for gout, but dehydration is.
- Start the Siddha pathiyam your physician sets — usually warm, freshly cooked, low-fructose food.
Weeks 5–8: rebuild metabolic flexibility
- Build to 150 minutes of moderate activity a week — brisk walking, cycling, swimming.
- Add resistance training twice a week. Muscle is the largest glucose sink you own.
- Target 0.5–1% body-weight loss per week; rapid crash dieting can transiently raise urate.
- Protect sleep: 7–8 hours, consistent timing. Short sleep worsens insulin resistance.
- Continue herbal therapy and begin gentle thokkanam once inflammation has settled.
Weeks 9–12: consolidate and re-test
- Repeat serum urate, fasting glucose, HbA1c, lipids and kidney function.
- Review flare frequency and joint mobility with your physician.
- Adjust the Siddha prescription and the pathiyam based on the new numbers.
- If urate is still high, discuss urate-lowering therapy with your doctor — the decision is clinical, not ideological.
If weight and blood sugar are the main drivers in your case, the weight management programme and the 3F Protocol at Mayura are built around exactly this sequence. For the weight-loss side in more depth, see our guide to Siddha medicine for weight loss, and for the liver-and-metabolism angle, Siddha medicine for fatty liver.
Gout Diet for Indian Professionals
What to cut, what to keep
- Cut hard: beer and spirits, sugar-sweetened sodas and juices, high-fructose syrups, organ meats, and shellfish.
- Cut back: red meat, prawns, and very large portions of any meat at a single sitting.
- Keep: dal, rajma, chana, paneer, curd and vegetables. Plant purines do not raise gout risk the way meat and alcohol do — this is one of the most persistent myths in Indian gout advice.
- Add: 2.5–3 litres of water, coffee (2 cups), vitamin C-rich fruit, and low-fat dairy, which is mildly protective.
- Watch: crash diets and fasting longer than 16 hours can spike urate in the short term.
A sample day
Morning: warm water, then 2 idlis with sambar and papaya. Lunch: 2 rotis, dal, a green vegetable, curd and salad. Afternoon: buttermilk instead of a cold drink. Evening: roasted chana. Dinner: khichdi or millet upma with vegetables, finished before 8:30 p.m. Nothing exotic — the point is consistency and hydration, not restriction.
Safety, Interactions and Red Flags
- Never stop allopurinol or febuxostat on your own to "try herbs". Stopping urate-lowering therapy abruptly can trigger a severe flare.
- Tell your Siddha physician every medicine you take — diuretics, low-dose aspirin, TB medication and some blood-pressure drugs all raise urate.
- Metallic parpam and mezhugu preparations must come from a qualified practitioner with quality-assured sourcing, never from an online seller.
- Pregnancy, breastfeeding, kidney disease and liver disease need physician-supervised care and different prescriptions.
- Seek urgent care for a hot swollen joint with fever, or if you cannot bear weight at all.
Frequently Asked Questions
Can Siddha medicine cure gout permanently?
No system of medicine "cures" the underlying tendency — gout is a metabolic condition that can be controlled. With sustained weight loss, alcohol and fructose reduction, good hydration and supervised treatment, many people go years without a flare and can keep urate in range. That is control, and it is a genuinely good outcome.
How long does Siddha treatment for gout take to work?
Acute pain relief is usually conventional and fast — hours to a few days. Metabolic change is slower: most people notice fewer and milder flares within 8–12 weeks, while serum urate and any tophi take several months to a year to respond fully.
Can I take Siddha medicines along with allopurinol?
Often yes, but only under supervision. Your physician needs to know both prescriptions, and urate and kidney function should be monitored. Never adjust a conventional prescription without your doctor.
Does gout mean I will get diabetes?
Not automatically, but the two share a root. High urate is strongly associated with insulin resistance and metabolic syndrome, so a gout diagnosis is a good reason to check fasting glucose, HbA1c and lipids — and to act on them early.
Related reading: our gout and uric acid treatment page, the guide to diabetes care at Mayura, and how the 3F Protocol structures metabolic recovery.
Stop Treating the Toe. Start Treating the Cause.
At Mayura Hospitals, gout is assessed as what it usually is — a metabolic condition with a joint symptom. You get a root-cause evaluation, a personalised pathiyam and Siddha treatment plan, and your urate, glucose and lipid markers tracked properly over 12 weeks.
This article is for general information and does not replace individual medical advice. Gout should be diagnosed and treated by a qualified physician. Do not start, stop or change any medication or herbal formulation without medical supervision.
Key Takeaways
- Evidence-based insights from our medical experts
- Practical steps you can apply to your health journey
- Part of our commitment to metabolic health education
Written by
Dr. Mayura
Healthcare professional at Mayura Hospitals, specializing in metabolic health and the 3F Protocol.